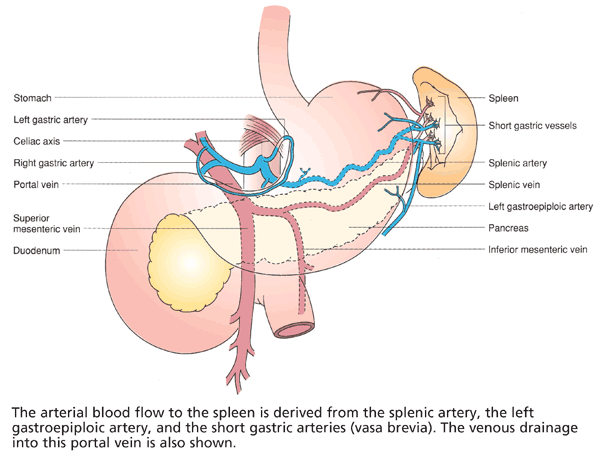
Short gastrics and splenic artery are end arteries
 Splenic vein is posterior and inferior to the splenic artery
 Spleen serves as an antigen-processing center for macrophages
 Is the largest producer of IgM
 85% red pulp – acts as a filter for aged or damaged RBCs
• Pitting – removal of abnormalities in RBC membrane
• Howell–Jolly bodies – nuclear remnants
• Heinz bodies – hemoglobin
• Culling – removal of less deformable RBCs
 15% white pulp – immunologic function; contains lymphocytes and macrophages
• Major site of bacterial clearance that lacks preexisting antibodies
• Site of removal of poorly opsonized bacteria, particles, and cellular debris
• Antigen processing occurs with interaction between macrophages and helper T cells
 Tuftsin – an opsonin; facilitates phagocytosis → produced in spleen
 Properdin – activates alternate complement pathway → produced in spleen
 Hematopoiesis – occurs in spleen before birth and in conditions such as myeloid dysplasia
 Spleen serves as a reservoir for platelets
 Accessory spleen (20%) – most commonly found at splenic hilum
 Indication for splenectomy – idiopathic thrombocytopenic purpura (ITP) far greater than for thrombotic thrombocytopenic purpura (TTP)
 ITP most common nontraumatic condition requiring splenectomy
IDIOPATHIC THROMBOCYTOPENIC PURPURA (ITP)
 This can occur from many etiologies – drugs, viruses, etc.
 Caused by anti-platelet antibodies (IgG) – bind platelets; results in decreased platelets
 Petechiae, gingival bleeding, bruising, soft tissue ecchymosis
 Spleen is normal
 In children < 10 years, ITP usually resolves spontaneously (avoid splenectomy in children)
 Tx: steroids (primary therapy); gammaglobulin if steroid resistant
 Splenectomy indicated for those who fail steroids removes IgG production and source of phagocytosis; 80% respond after splenectomy
 Give platelets 1 hour before surgery
THROMBOTIC THROMBOCYTOPENIC PURPURA (TTP)
 Associated with medical reactions, infections, inflammation, autoimmune disease
 Loss of platelet inhibition – leads to thrombosis and infarction, profound thrombocytopenia
 Purpura, fever, mental status changes, renal dysfunction, hematuria, hemolytic anemia
 80% respond to medical therapy
 Tx: plasmapheresis (primary); immunosuppression
 Death most commonly due to intracerebral hemorrhage or acute renal failure
 Splenectomy rarely indicated
POST-SPLENECTOMY SEPSIS SYNDROME (PSSS)
 0.1% risk after splenectomy; ↑ risk in children
 S. pneumoniae (#1), H. influenzae, N. meningitidis – most common
 Secondary to specific lack of immunity (immunoglobulin, IgM) to capsulated bacteria
 Highest in patients with splenectomy for hemolytic disorders or malignancy
 Children also have ↑ risk of mortality after developing PSSS
 Try to wait until at least 5 years old before performing splenectomy → allows antibody formation; child can get fully immunized
 Most episodes occur within 2 years of splenectomy
 Children < 10 years should be given prophylactic antibiotics for 6 months (controversial)
 Vaccines needed before splenectomy – Pneumococcus, Meningococcus, H. influenzae


Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


