Epidermis – primarily cellular
• Keratinocytes – main cell type in epidermis; originate from basal layer; provide mechanical barrier
• Melanocytes – neuroectodermal origin (neural crest cells); in basal layer of epidermis
• Have dendritic processes that transfer melanin to neighboring keratinocytes via melanosomes
• Density of melanocytes is the same among races; difference is in melanin production
 Dermis – primarily structural proteins (collagen) for the epidermis
 Langerhans cells
• Act as antigen-presenting cells (MHC class II)
• Originate from bone marrow
• Have a role in contact hypersensitivity reactions (type IV)
 Sensory nerves
• Pacinian corpuscles – pressure
• Ruffini’s endings – warmth
• Krause’s end-bulbs – cold
• Meissner’s corpuscles – tactile sense
 Eccrine sweat glands – aqueous sweat (thermal regulation, usually hypotonic)
 Apocrine sweat glands – milky sweat
• Highest concentration of glands in palms and soles; most sweat is the result of sympathetic nervous system via acetylcholine
 Lipid-soluble drugs – ↑ skin absorption
 Type I collagen – predominant type in skin; 70% of dermis; gives tensile strength
 Tension – resistance to stretching (collagen)
 Elasticity – ability to regain shape (branching proteins that can stretch to 2× normal length)
 Cushing’s striae – caused by loss of tensile strength and elasticity
FLAPS
 MCC of pedicled or anastomosed free flap necrosis – venous thrombosis
 Tissue expansion occurs by local recruitment, thinning of the dermis and epidermis, mitosis
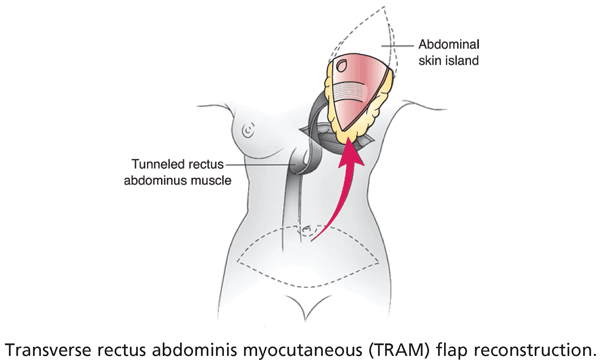
 TRAM flaps
• Complications – flap necrosis, ventral hernia, bleeding, infection, abdominal wall weakness
• Rely on superior epigastric vessels
• Periumbilical perforators most important determinant of TRAM flap viability

UV RADIATION
 Damages DNA and repair mechanisms
 Both a promoter and initiator
 Melanin single best factor for protecting skin from UV radiation
 UV-B – responsible for chronic sun damage
MELANOMA
 Represents only 5% of skin CA but accounts for 65% of the deaths
 Risk factors for melanoma:
• Dysplastic, atypical, or large congenital nevi – 10% lifetime risk for melanoma
• Familial BK mole syndrome – almost 100% risk of melanoma
• Xeroderma pigmentosum
• Fair complexion, easy sunburn, intermittent sunburns, previous skin CA, previous XRT
• 10% of melanomas familial
 Most common melanoma site on skin – back in men, legs in women
 Prognosis worse for men, ulcerated lesions, ocular and mucosal lesions
 Signs of melanoma (ABCDE) – asymmetry (angulations, indentation, notching, ulceration, bleeding), borders that are irregular, color change (darkening), diameter increase, evolving over time
 Originates from neural crest cells (melanocytes) in basal layer epidermis
 Blue color → most ominous
 Lung – most common location for distant melanoma metastases
 Most common metastasis to small bowel – melanoma
 Dx:
• < 2 cm lesion – excisional biopsy (tru-cut core needle biopsy) unless cosmetically sensitive area – need resection with margins if pathology comes back as melanoma
• > 2 cm lesions or cosmetically sensitive area – incisional biopsy (or punch biopsy), will need to resect with margins if pathology shows melanoma
 Types:
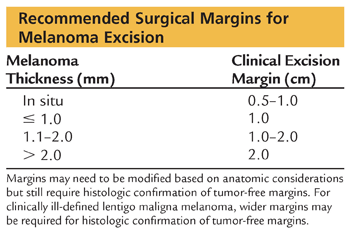
• Melanoma in situ or thin lentigo maligna (Hutchinson’s freckle) – just in the superficial papillary dermis; 0.5-cm margins OK
• Lentigo maligna melanoma – least aggressive, minimal invasion, radial growth 1st usual; elevated nodules
• Superficial spreading melanoma – most common, intermediate malignancy; originates from nevus/sun-exposed areas
• Nodular – most aggressive; most likely to have metastasized at time of diagnosis; deepest growth at time of diagnosis; vertical growth 1st; bluish-black with smooth borders; occurs anywhere on the body
• Acral lentiginous – very aggressive; palms/soles of African Americans
 Staging – chest/abd/pelvic CT, LFTs, and LDH for all melanoma ≥ 1 mm; examine all possible draining lymph nodes
 Tx for all stages → 1) resection of primary tumor with appropriate margins and; 2) management of lymph nodes

Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


