

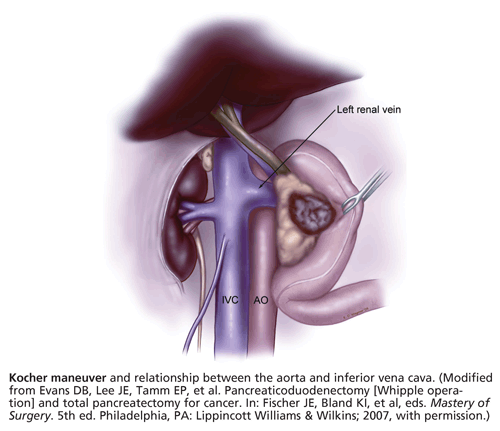
 Head (including uncinate), neck, body, and tail
 Uncinate process – rests on aorta, behind SMV
 SMV and SMA – lay behind neck of pancreas
 Portal vein – forms behind the neck (SMV and splenic vein)
 Blood supply
• Head – superior (off GDA) and inferior (off SMA) pancreaticoduodenal arteries (anterior and posterior branches for each)
• Body – great, inferior, and caudal pancreatic arteries (all off splenic artery)
• Tail – splenic, gastroepiploic, and dorsal pancreatic arteries
 Venous drainage into the portal system
 Lymphatics – celiac and SMA nodes
 Ductal cells – secrete HCO3− solution (have carbonic anhydrase)
 Acinar cells – secrete digestive enzymes
 Exocrine function of the pancreas – amylase, lipase, trypsinogen, chymotrypsinogen, carboxypeptidase; HCO3−
• Amylase – only pancreatic enzyme secreted in active form; hydrolyzes alpha 1–4 linkages of glucose chains
 Endocrine function of the pancreas
• Alpha cells – glucagon
• Beta cells (at center of islets) – insulin
• Delta cells – somatostatin
• PP or F cells – pancreatic polypeptide
• Islet cells – also produce vasoactive intestinal peptide (VIP), serotonin
 Islet cells receive majority of blood supply related to size
• After islets, blood goes to acinar cells
 Enterokinase – released by the duodenum, activates trypsinogen to trypsin
• Trypsin activates other pancreatic enzymes including trypsinogen
 Hormonal control of pancreatic excretion
• Secretin – ↑ HCO3− mostly
• CCK – ↑ pancreatic enzymes mostly
• Acetylcholine – ↑ HCO− and enzymes
• Somatostatin and glucagons – ↓ exocrine function
• CCK and secretin – most released by cells in the duodenum
 Ventral pancreatic bud
• Connected to duct of Wirsung; migrates posteriorly, to the right, and clockwise to fuse with the dorsal bud
• Forms uncinate and inferior portion of the head
 Dorsal pancreatic bud – body, tail, and superior aspect of the pancreatic head; has duct of Santorini
 Duct of Wirsung – major pancreatic duct that merges with CBD before entering duodenum
 Duct of Santorini – small accessory pancreatic duct that drains directly into duodenum
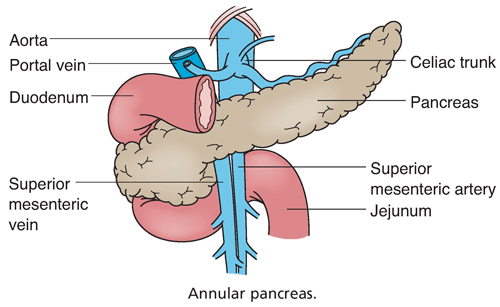
ANNULAR PANCREAS
 2nd portion of duodenum trapped in pancreatic band; can see double bubble on abdominal x-ray; get duodenal obstruction (N/V, abdominal pain)
 Associated with Down syndrome; forms from the ventral pancreatic bud from failure of clockwise rotation
 Tx: duodenojejunostomy or duodenoduodenostomy; possible sphincteroplasty
• Pancreas not resected
PANCREAS DIVISUM
 Failed fusion of the pancreatic ducts; can result in pancreatitis from duct of Santorini (accessory duct) stenosis
 Most are asymptomatic; some get pancreatitis
 Dx: ERCP – minor papilla will show long and large duct of Santorini; major papilla will show short duct of Wirsung
 Tx: ERCP with sphincteroplasty; open sphincteroplasty if that fails
HETEROTOPIC PANCREAS
 Most commonly found in duodenum
 Usually asymptomatic
 Surgical resection if symptomatic
ACUTE PANCREATITIS
 Gallstones and ETOH most common etiologies in the United States
• Other etiologies – ERCP, trauma, hyperlipidemia, hypercalcemia, viral infection, medications (azathioprine, furosemide, steroids, cimetidine)
• Gallstones – can obstruct the ampulla of Vater, causing impaired extrusion of zymogen granules and activation of degradation enzymes → leads to pancreatic auto-digestion
• ETOH – can cause auto-activation of pancreatic enzymes while still in the pancreas
 Symptoms: abdominal pain radiating to the back, nausea, vomiting, anorexia
• Can also get jaundice, left pleural effusion, ascites, or sentinel loop (dilated small bowel near the pancreas as a result of the inflammation)
 Mortality rate 10%; hemorrhagic pancreatitis mortality 50%
 Pancreatitis without obvious cause → need to worry about malignancy
 Ranson’s criteria
• On admission → age > 55, WBC > 16, glucose > 200, AST > 250, LDH > 350
• After 48 hours: Hct ↓ 10%, BUN ↑ of 5, Ca < 8, PaO2 < 60, base deficit > 4, fluid sequestration > 6 L
• 8 Ranson criteria met → mortality rate near 100%
 Labs: ↑ amylase, lipase, and WBCs
 Ultrasound – needed to check for gallstones and possible CBD dilatation
 Abdominal CT – to check for complications (necrotic pancreas will not uptake contrast)
 Tx: NPO, aggressive fluid resuscitation
• ERCP is needed in patients with gallstone pancreatitis and retained CBD stones → perform sphincterotomy and stone extraction
• Antibiotics for stones, severe pancreatitis, failure to improve, or suspected infection
• TPN may be necessary during recovery period
• Patients with gallstone pancreatitis should undergo cholecystectomy when recovered from pancreatitis (same hospital admission)
• Morphine should be avoided as it can contract the sphincter of Oddi and worsen attack
 Bleeding
• Grey Turner sign – flank ecchymosis
• Cullen’s sign – periumbilical ecchymosis
• Fox’s sign – inguinal ecchymosis
 15% get pancreatic necrosis – leave sterile necrosis alone
• Infected necrosis (fever, sepsis, positive blood cultures; may need to sample necrotic pancreatic fluid with CT-guided aspiration to get diagnosis) Tx: need surgical debridement
• Pancreatic abscesses → Tx: need surgical debridement
• CT-guided drainage of infected pancreatic necrosis or pancreatic abscess is generally not effective
• Gas in necrotic pancreas = infected necrosis or abscess (need open debridement)
 Infection – leading cause of death with pancreatitis; usually GNRs
 Surgery only for infected pancreatitis or pancreatic abscess
 Obesity – most important risk factor for necrotizing pancreatitis
 ARDS – related to release of phospholipases
 Coagulopathy – related to release of proteases
 Pancreatic fat necrosis – related to release of phospholipases
 Mild ↑ amylase and lipase can be seen with cholecystitis, perforated ulcer, sialoadenitis, small bowel obstruction (SBO), and intestinal infarction
PANCREATIC PSEUDOCYSTS
 Most common in patients with chronic pancreatitis
• Cysts not associated with pancreatitis – need to R/O CA (eg mucinous cystadenocarcinoma)
 Symptoms: pain, fever, weight loss, bowel obstruction from compression
 Often occurs in the head of the pancreas; is a non-epithelialized sac
 Most resolve spontaneously (especially if < 5 cm)
 Tx: expectant management for 3 months – (most resolve on their own; also allows pseudocyst to mature if cystogastrostomy is required)
• May need to place these patients on TPN if unable to eat
• Surgery only for continued symptoms (Tx: cystogastrostomy, open or percutaneous) or pseudocysts that are growing (Tx: resection to R/O CA)
 Complications of pancreatic pseudocyst – infection of cyst, portal or splenic vein thrombosis
 Incidental cysts not associated with pancreatitis should be resected (worry about intraductal papillary-mucinous neoplasms [IPMNs] or mucinous cystadenocarcinoma) unless the cyst is purely serous and non-complex
 Non-complex, purely serous cystadenomas have an extremely low malignancy risk (< 1%) and can be followed
PANCREATIC FISTULAS
 Most close spontaneously (especially if low output < 200 cc/day)
 Tx: allow drainage, NPO, TPN, octreotide
• If failure to resolve with medical management, can try ERCP, sphincterotomy, and pancreatic stent placement (fistula will usually close, then remove stent)
PANCREATITIS-ASSOCIATED PLEURAL EFFUSION (OR ASCITES)
 Caused by retroperitoneal leakage of pancreatic fluid from the pancreatic duct or a pseudocyst (is not a pancreatic–pleural fistula); majority close on their own
 Tx: thoracentesis (or paracentesis) followed by conservative Tx (NPO, TPN, and octreotide – follow pancreatic fistula pathway above)
• Amylase will be elevated in the fluid
CHRONIC PANCREATITIS
 Corresponds to irreversible parenchymal fibrosis
 ETOH most common cause; idiopathic 2nd most common
 Pain most common problem; anorexia, weight loss, malabsorption, steatorrhea, recurrent acute pancreatitis
 Endocrine function usually preserved (Islet cell preserved); exocrine function decreased
 Can cause malabsorption of fat-soluble vitamins (Tx: pancrelipase)
 Dx: abdominal CT will show shrunken pancreas with calcifications
• Ultrasound – shows pancreatic ducts > 4 mm, cysts, and atrophy

Stay updated, free articles. Join our Telegram channel

Full access? Get Clinical Tree


